
天津医药 ›› 2026, Vol. 54 ›› Issue (11): 1183-1188.doi: 10.11958/20260606
黄建会( ), 李兰兰, 刘承丽△()
收稿日期:2026-03-04
修回日期:2026-05-25
出版日期:2026-11-15
发布日期:2026-11-10
通讯作者:
李兰兰,刘承丽
E-mail:15892944597@163.com;1012554788@qq.com
作者简介:黄建会(1977),女,副主任医师,主要从事重症医学方面研究。E-mail:15892944597@163.com
基金资助:
HUANG Jianhui(), LI Lanlan, LIU Chengli△()
Received:2026-03-04
Revised:2026-05-25
Published:2026-11-15
Online:2026-11-10
Contact:
LI Lanlan, LIU Chengli
E-mail:15892944597@163.com;1012554788@qq.com
黄建会, 李兰兰, 刘承丽. ARDS患者早期肠内营养不耐受的列线图预测模型构建[J]. 天津医药, 2026, 54(11): 1183-1188.
HUANG Jianhui, LI Lanlan, LIU Chengli. Construction of a nomogram prediction model for early enteral nutrition intolerance in patients with ARDS[J]. Tianjin Medical Journal, 2026, 54(11): 1183-1188.
摘要:
目的 基于C反应蛋白/白蛋白比值(CAR)、中性粒细胞/淋巴细胞比值(NLR)、预后营养指数(PNI)以及临床特征构建急性呼吸窘迫综合征(ARDS)患者早期肠内营养不耐受的列线图预测模型。方法 采用回顾性队列研究设计,选取2021年5月—2025年5月我院收治的395例接受肠内营养支持的ARDS患者。依据住院期间早期肠内营养不耐受发生情况,分为不耐受组(139例)和耐受组(256例)。收集患者临床资料及实验室指标,计算CAR、NLR和PNI。多因素Logistic回归分析筛选独立影响因素,并据此构建列线图模型。采用受试者工作特征(ROC)曲线、校准曲线(Hosmer-Lemeshow检验)和决策曲线分析(DCA)分别评价模型的区分度、校准度和临床净收益。结果 不耐受组CAR、NLR高于耐受组,PNI低于耐受组(均P<0.05)。多因素Logistic回归分析结果显示,CAR、NLR、急性生理与慢性健康状况评估Ⅱ(APACHE Ⅱ)评分升高是ARDS患者早期肠内营养不耐受的危险因素(P<0.05),PNI、氧合指数(OI)、平均动脉压(MAP)升高是保护因素(P<0.05)。基于上述因素构建列线图预测模型,ROC曲线分析显示,模型预测早期肠内营养不耐受的曲线下面积为0.866(95%CI:0.830~0.902);校准曲线显示,模型拟合度良好(Hosmer-Lemeshow χ2=4.273,P=0.832);DCA结果表明,模型在0.02~0.80阈值范围内具有显著临床净收益。结论 基于CAR、NLR及PNI构建的列线图预测模型能有效预测ARDS患者早期肠内营养不耐受风险。
中图分类号:
| 组别 | n | 年龄/岁 | 性别 | 体质量 指数/(kg/m²) | 吸烟史 | 饮酒史 | 基础病 | 既往慢性 胃肠疾病 | 使用胃肠 动力药物 | ||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 男 | 女 | 糖尿病 | 高血压 | 高脂血症 | |||||||||||||||||||||||||||||||||||||
| 耐受组 | 256 | 62.16±9.99 | 162(63.28) | 94(36.72) | 23.83±3.87 | 102(39.84) | 95(37.11) | 147(57.42) | 135(52.73) | 123(48.05) | 25(9.77) | 98(38.28) | |||||||||||||||||||||||||||||
| 不耐受组 | 139 | 69.00±8.24 | 89(64.03) | 50(35.97) | 23.52±3.39 | 51(36.69) | 47(33.81) | 82(58.99) | 76(54.68) | 65(46.76) | 28(20.14) | 65(46.76) | |||||||||||||||||||||||||||||
| t或χ2 | 6.902** | 0.022 | 0.801 | 0.377 | 0.091 | 0.091 | 0.137 | 0.060 | 8.352** | 2.674 | |||||||||||||||||||||||||||||||
| 组别 | ARDS病因 | 呼吸支持方式 | 肠内营养启动时间 | ||||||||||||||||||||||||||||||||||||||
| 脓毒症 | 创伤 | 严重肺部感染 | 其他 | 无创通气 | 有创机械通气 | 高流量吸氧 | 发病48 h内 | 发病48~72 h内 | |||||||||||||||||||||||||||||||||
| 耐受组 | 120(46.88) | 40(15.62) | 85(33.20) | 11(4.30) | 62(24.22) | 180(70.31) | 14(5.47) | 196(76.56) | 60(23.44) | ||||||||||||||||||||||||||||||||
| 不耐受组 | 75(53.96) | 18(12.95) | 41(29.50) | 5(3.60) | 25(17.99) | 102(73.38) | 12(8.63) | 101(72.66) | 38(27.34) | ||||||||||||||||||||||||||||||||
| χ2 | 1.851 | 3.078 | 0.735 | ||||||||||||||||||||||||||||||||||||||
| 组别 | 喂养途径 | 肠内营养制剂类型 | 每日能量 供给量/(kJ/kg) | 营养支持持 续时间/d | APACHEⅡ 评分/分 | SOFA 评分/分 | |||||||||||||||||||||||||||||||||||
| 鼻胃管 | 鼻肠管 | 整蛋白型 | 短肽型 | 要素型 | |||||||||||||||||||||||||||||||||||||
| 耐受组 | 225(87.89) | 31(12.11) | 215(83.98) | 36(14.06) | 5(1.95) | 89.19±16.35 | 8(6,10) | 19.74±5.01 | 7.31±1.95 | ||||||||||||||||||||||||||||||||
| 不耐受组 | 125(89.93) | 14(10.07) | 110(79.14) | 25(17.99) | 4(2.88) | 87.76±15.55 | 8(5,10) | 24.54±5.99 | 9.09±2.12 | ||||||||||||||||||||||||||||||||
| χ2 | 0.370 | 1.493 | 0.845 | 0.544 | 8.483** | 8.385** | |||||||||||||||||||||||||||||||||||
| 组别 | MAP/mmHg | OI/mmHg | 白细胞计数/(×10⁹/L) | 血小板计数/(×10⁹/L) | ALT/(U/L) | AST/(U/L) | |||||||||||||||||||||||||||||||||||
| 耐受组 | 78.74±10.03 | 153.87±43.24 | 13.09±4.29 | 192.55±33.12 | 42.32(30.25,65.19) | 50.32(35.16,78.92) | |||||||||||||||||||||||||||||||||||
| 不耐受组 | 67.70±9.03 | 115.44±33.20 | 13.51±4.63 | 192.93±23.72 | 45.02(32.05,78.18) | 51.32(38.15,95.67) | |||||||||||||||||||||||||||||||||||
| t或Z | 10.819** | 9.119** | 0.921 | 0.120 | 0.510 | 0.970 | |||||||||||||||||||||||||||||||||||
| 组别 | 血肌酐/(μmol/L) | 尿素氮/(mmol/L) | 血钾/(mmol/L) | 血钠/(mmol/L) | 空腹血糖/(mmol/L) | 三酰甘油/(mmol/L) | |||||||||||||||||||||||||||||||||||
| 耐受组 | 85.66±22.10 | 8.89±2.07 | 3.50±0.51 | 135.60±4.85 | 7.33±2.16 | 1.72±0.42 | |||||||||||||||||||||||||||||||||||
| 不耐受组 | 86.54±21.29 | 8.81±2.15 | 3.42±0.64 | 135.73±5.66 | 7.61±2.04 | 1.75±0.33 | |||||||||||||||||||||||||||||||||||
| t | 0.384 | 0.327 | 1.395 | 0.244 | 1.259 | 0.577 | |||||||||||||||||||||||||||||||||||
表1 2组患者基线资料比较
Tab.1 Comparison of baseline data between the intolerance group and the tolerance group
| 组别 | n | 年龄/岁 | 性别 | 体质量 指数/(kg/m²) | 吸烟史 | 饮酒史 | 基础病 | 既往慢性 胃肠疾病 | 使用胃肠 动力药物 | ||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 男 | 女 | 糖尿病 | 高血压 | 高脂血症 | |||||||||||||||||||||||||||||||||||||
| 耐受组 | 256 | 62.16±9.99 | 162(63.28) | 94(36.72) | 23.83±3.87 | 102(39.84) | 95(37.11) | 147(57.42) | 135(52.73) | 123(48.05) | 25(9.77) | 98(38.28) | |||||||||||||||||||||||||||||
| 不耐受组 | 139 | 69.00±8.24 | 89(64.03) | 50(35.97) | 23.52±3.39 | 51(36.69) | 47(33.81) | 82(58.99) | 76(54.68) | 65(46.76) | 28(20.14) | 65(46.76) | |||||||||||||||||||||||||||||
| t或χ2 | 6.902** | 0.022 | 0.801 | 0.377 | 0.091 | 0.091 | 0.137 | 0.060 | 8.352** | 2.674 | |||||||||||||||||||||||||||||||
| 组别 | ARDS病因 | 呼吸支持方式 | 肠内营养启动时间 | ||||||||||||||||||||||||||||||||||||||
| 脓毒症 | 创伤 | 严重肺部感染 | 其他 | 无创通气 | 有创机械通气 | 高流量吸氧 | 发病48 h内 | 发病48~72 h内 | |||||||||||||||||||||||||||||||||
| 耐受组 | 120(46.88) | 40(15.62) | 85(33.20) | 11(4.30) | 62(24.22) | 180(70.31) | 14(5.47) | 196(76.56) | 60(23.44) | ||||||||||||||||||||||||||||||||
| 不耐受组 | 75(53.96) | 18(12.95) | 41(29.50) | 5(3.60) | 25(17.99) | 102(73.38) | 12(8.63) | 101(72.66) | 38(27.34) | ||||||||||||||||||||||||||||||||
| χ2 | 1.851 | 3.078 | 0.735 | ||||||||||||||||||||||||||||||||||||||
| 组别 | 喂养途径 | 肠内营养制剂类型 | 每日能量 供给量/(kJ/kg) | 营养支持持 续时间/d | APACHEⅡ 评分/分 | SOFA 评分/分 | |||||||||||||||||||||||||||||||||||
| 鼻胃管 | 鼻肠管 | 整蛋白型 | 短肽型 | 要素型 | |||||||||||||||||||||||||||||||||||||
| 耐受组 | 225(87.89) | 31(12.11) | 215(83.98) | 36(14.06) | 5(1.95) | 89.19±16.35 | 8(6,10) | 19.74±5.01 | 7.31±1.95 | ||||||||||||||||||||||||||||||||
| 不耐受组 | 125(89.93) | 14(10.07) | 110(79.14) | 25(17.99) | 4(2.88) | 87.76±15.55 | 8(5,10) | 24.54±5.99 | 9.09±2.12 | ||||||||||||||||||||||||||||||||
| χ2 | 0.370 | 1.493 | 0.845 | 0.544 | 8.483** | 8.385** | |||||||||||||||||||||||||||||||||||
| 组别 | MAP/mmHg | OI/mmHg | 白细胞计数/(×10⁹/L) | 血小板计数/(×10⁹/L) | ALT/(U/L) | AST/(U/L) | |||||||||||||||||||||||||||||||||||
| 耐受组 | 78.74±10.03 | 153.87±43.24 | 13.09±4.29 | 192.55±33.12 | 42.32(30.25,65.19) | 50.32(35.16,78.92) | |||||||||||||||||||||||||||||||||||
| 不耐受组 | 67.70±9.03 | 115.44±33.20 | 13.51±4.63 | 192.93±23.72 | 45.02(32.05,78.18) | 51.32(38.15,95.67) | |||||||||||||||||||||||||||||||||||
| t或Z | 10.819** | 9.119** | 0.921 | 0.120 | 0.510 | 0.970 | |||||||||||||||||||||||||||||||||||
| 组别 | 血肌酐/(μmol/L) | 尿素氮/(mmol/L) | 血钾/(mmol/L) | 血钠/(mmol/L) | 空腹血糖/(mmol/L) | 三酰甘油/(mmol/L) | |||||||||||||||||||||||||||||||||||
| 耐受组 | 85.66±22.10 | 8.89±2.07 | 3.50±0.51 | 135.60±4.85 | 7.33±2.16 | 1.72±0.42 | |||||||||||||||||||||||||||||||||||
| 不耐受组 | 86.54±21.29 | 8.81±2.15 | 3.42±0.64 | 135.73±5.66 | 7.61±2.04 | 1.75±0.33 | |||||||||||||||||||||||||||||||||||
| t | 0.384 | 0.327 | 1.395 | 0.244 | 1.259 | 0.577 | |||||||||||||||||||||||||||||||||||
| 组别 | n | CAR/(mg/g) | NLR | PNI |
|---|---|---|---|---|
| 耐受组 | 256 | 2.92±0.73 | 3.08±1.10 | 47.96±10.68 |
| 不耐受组 | 139 | 5.21±1.80 | 6.44±2.01 | 31.41±7.96 |
| t | 17.821** | 21.428** | 16.016** |
表2 2组患者的CAR、NLR及PNI比较($\bar{x}±s$)
Tab.2 Comparison of CAR, NLR and PNI between the intolerance group and the tolerance group
| 组别 | n | CAR/(mg/g) | NLR | PNI |
|---|---|---|---|---|
| 耐受组 | 256 | 2.92±0.73 | 3.08±1.10 | 47.96±10.68 |
| 不耐受组 | 139 | 5.21±1.80 | 6.44±2.01 | 31.41±7.96 |
| t | 17.821** | 21.428** | 16.016** |
| 变量 | β | SE | Wald χ2 | P | OR(95%CI) |
|---|---|---|---|---|---|
| CAR | 0.145 | 0.062 | 5.470 | 0.019 | 1.156(1.024~1.305) |
| NLR | 0.286 | 0.097 | 8.693 | 0.003 | 1.331(1.101~1.610) |
| APACHEⅡ评分 | 0.178 | 0.085 | 4.385 | 0.036 | 1.194(1.011~1.411) |
| PNI | -0.151 | 0.039 | 14.980 | <0.001 | 0.860(0.796~0.929) |
| OI | -0.018 | 0.009 | 4.000 | 0.046 | 0.982(0.965~0.999) |
| MAP | -0.182 | 0.067 | 7.379 | 0.007 | 0.834(0.731~0.951) |
| 常数项 | 1.250 | 0.520 | 5.785 | 0.016 | 3.490 |
表3 ARDS患者发生早期肠内营养不耐受的Logistic因素分析
Tab.3 Analysis of factors for early enteral nutrition intolerance in patients with ARDS
| 变量 | β | SE | Wald χ2 | P | OR(95%CI) |
|---|---|---|---|---|---|
| CAR | 0.145 | 0.062 | 5.470 | 0.019 | 1.156(1.024~1.305) |
| NLR | 0.286 | 0.097 | 8.693 | 0.003 | 1.331(1.101~1.610) |
| APACHEⅡ评分 | 0.178 | 0.085 | 4.385 | 0.036 | 1.194(1.011~1.411) |
| PNI | -0.151 | 0.039 | 14.980 | <0.001 | 0.860(0.796~0.929) |
| OI | -0.018 | 0.009 | 4.000 | 0.046 | 0.982(0.965~0.999) |
| MAP | -0.182 | 0.067 | 7.379 | 0.007 | 0.834(0.731~0.951) |
| 常数项 | 1.250 | 0.520 | 5.785 | 0.016 | 3.490 |

图1 ARDS患者发生早期肠内营养不耐受预测模型列线图
Fig.1 Nomogram model for early enteral nutrition intolerance in ARDS patients
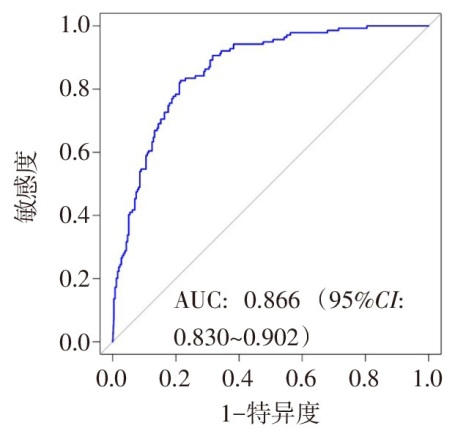
图2 列线图模型预测ARDS患者发生早期肠内营养不耐受的ROC曲线
Fig.2 ROC curve of the nomogram model for predicting early enteral nutrition intolerance in patients with ARDS
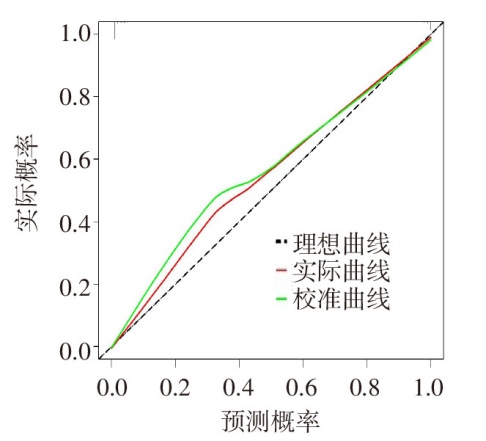
图3 ARDS患者发生早期肠内营养不耐受列线图模型的校准曲线
Fig.3 Calibration curve of the nomogram model for early enteral nutrition intolerance in ARDS patients
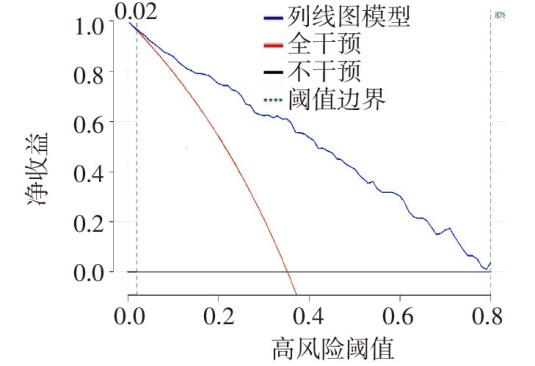
图4 ARDS患者发生早期肠内营养不耐受列线图模型的DCA曲线
Fig.4 Nomogram model DCA curve illustrating early enteral nutrition intolerance in ARDS patients
| [1] | 卫路得, 任艺, 李亮, 等. 早期肠内营养联合益生菌对急性呼吸窘迫综合征患者预后的影响[J]. 中国微生态学杂志, 2023, 35(6):713-716. |
| Wei L D, Ren Y, Li L, et al. Effects of early enteral nutrition combined with probiotics on prognoses of patients with acute respiratory distress syndrome[J]. Chin J Microecol, 2023, 35(6):713-716. doi:10.13381/j.cnki.cjm.202306014. | |
| [2] | 路明顺, 刘泽玉, 张会敏. 早期液体管理联合肠内营养支持在急性呼吸窘迫综合征中应用效果[J]. 临床研究, 2024, 32(2):42-45. |
| Lu M S, Liu Z Y, Zhang H M. Application effect of early liquid management combined with enteral nutrition support in acute respiratory distress syndrome[J]. Clinical Research, 2024, 32(2):42-45. doi:10.12385/j.issn.2096-1278(2024)02-0042-04. | |
| [3] | 朴鲜女, 许惠仙. 不同肠内营养对急性呼吸窘迫综合征患者营养状况和炎症水平及免疫功能的影响[J]. 中国中西医结合急救杂志, 2024, 31(1):73-76. |
| Piao X N, Xu H X. Effect of different enteral nutrition on nutrition and inflammation and immunity function in patients with acute respiratory distress syndrome[J]. Chinese Journal of Integrated Traditional and Western Medicine in Intensive and Critical Care, 2024, 31(1):73-76. doi:10.3969/j.issn.1008-9691.2024.01.015. | |
| [4] | Xiao W, Zeng Y, Ai L, et al. Clinical predictors and prevalence of enteral nutrition intolerance in acute pancreatitis:an updated systematic review and meta-analysis[J]. Nutrients, 2025, 17(5):910. doi:10.3390/nu17050910. |
| [5] | 袁计红, 金咏梅, 袁玲红. 全程营养管理对危重症患者胃肠不耐受及生存质量的影响[J]. 重庆医学, 2024, 53(S01):51-54. |
| Yuan J H, Jin Y M, Yuan L H. The influence of whole-course nutritional management on gastrointestinal intolerance and quality of life in critically ill patients[J]. Chongqing Medicine, 2024, 53(S01):51-54. | |
| [6] | 刘鑫雨. 血清C反应蛋白/白蛋白比值在重症急性胰腺炎患者早期肠内营养喂养不耐受中的预测价值[D]. 十堰: 湖北医药学院, 2025. |
| Liu X Y. Predictive value of serum C-reactive protein to albumin ratio for feeding intolerance of early enteral nutrition in patients with severe acute pancreatitis[D]. Shiyan: Hubei University of Medicine, 2025. | |
| [7] | Nie S, Wang H, Liu Q, et al. Prognostic value of neutrophils to lymphocytes and platelets ratio for 28-day mortality in patients with acute respiratory distress syndrome:a retrospective study[J]. BMC Pulm Med, 2022, 22(1):314. doi:10.1186/s12890-022-02112-w. |
| [8] | Wang M, Li W, Xu H, et al. The Relation between the prognostic nutritional index and 30-day mortality in patients with acute respiratory distress syndrome:a retrospective study based on the MIMIC-IV Database[J]. J Surg Res, 2025, 312:204-213. doi:10.1016/j.jss.2025.05.021. |
| [9] | ARDS Definition Task Force, Ranieri V M, Rubenfeld G D, et al. Acute respiratory distress syndrome:the Berlin Definition[J]. JAMA, 2012, 307(23):2526-2533. doi:10.1001/jama.2012.5669. |
| [10] | Reintam Blaser A, Malbrain M L, Starkopf J, et al. Gastrointestinal function in intensive care patients:terminology,definitions and management. Recommendations of the ESICM Working Group on Abdominal Problems[J]. Intensive Care Med, 2012, 38(3):384-394. doi:10.1007/s00134-011-2459-y. |
| [11] | Knaus W A, Draper E A, Wagner D P, et al. APACHE II:a severity of disease classification system[J]. Crit Care Med, 1985, 13(10):818-829. |
| [12] | Ferreira F L, Bota D P, Bross A, et al. Serial evaluation of the SOFA score to predict outcome in critically ill patients[J]. JAMA, 2001, 286(14):1754-1758. doi:10.1001/jama.286.14.1754. |
| [13] | Çelikkol A, Güzel E Ç, Doğan M, et al. C-reactive protein-to-albumin ratio as a prognostic inflammatory marker in COVID-19[J]. J Lab Physicians, 2022, 14(1):74-83. doi:10.1055/s-0041-1741439. |
| [14] | Hoffmeister B, Aguilar Valdez A D. Elevated admission C-reactive protein to albumin ratios are associated with disease severity and respiratory complications in adults with imported falciparum malaria[J]. Trans R Soc Trop Med Hyg, 2022, 116(5):492-500. doi:10.1093/trstmh/trab167. |
| [15] | Feng W, Zhu L, Liu Y, et al. C-reactive protein/albumin ratio and IL-6 are associated with disease activity in patients with ulcerative colitis[J]. J Clin Lab Anal, 2023, 37(3):e24843. doi:10.1002/jcla.24843. |
| [16] | Kaçer İ, Çağlar A, Akıllı N B. The prognostic value of C-reactive protein/albumin ratio in acute mesenteric ischemia[J]. Am Surg, 2023, 89(5):1661-1667. doi:10.1177/00031348221074220. |
| [17] | Hu K, Deng X L, Han L, et al. Development and validation of a predictive model for feeding intolerance in intensive care unit patients with sepsis[J]. Saudi J Gastroenterol, 2022, 28(1):32-38. doi:10.4103/sjg.sjg_286_21. |
| [18] | Solomon O M, Gu Y, Wei Y. Risk factors for enteral nutrition feeding intolerance in stroke patients:a scoping review[J]. Nurs Crit Care, 2025, 30(3):e13183. doi:10.1111/nicc.13183. |
| [19] | Bano Mehdi K, Jehan S, Akhter M, et al. Utility of neutrophil to lymphocyte ratio to predict acute respiratory distress syndrome in COVID-19:short communication[J]. Ann Med Surg (Lond), 2023, 85(6):3232-3236. doi:10.1097/MS9.0000000000000758. |
| [20] | Huang J, Liao F, Luo Y, et al. Neutrophil-to-lymphocyte ratio at admission is a risk factor for in-hospital gastrointestinal bleeding in acute ischemic stroke patients after dual antiplatelet therapy:a case control study[J]. J Stroke Cerebrovasc Dis, 2023, 32(10):107325. doi:10.1016/j.jstrokecerebrovasdis.2023.107325. |
| [21] | Wang S, Song Y, Wang Z, et al. Neutrophil-derived PAD4 induces citrullination of CKMT1 exacerbates mucosal inflammation in inflammatory bowel disease[J]. Cell Mol Immunol, 2024, 21(6):620-633. doi:10.1038/s41423-024-01158-6. |
| [22] | Wang Z, Wang J. Innate lymphoid cells and gastrointestinal disease[J]. J Genet Genomics, 2021, 48(9):763-770. doi:10.1016/j.jgg.2021.08.004. |
| [23] | Bodolea C, Nemes A, Avram L, et al. Nutritional risk assessment scores effectively predict mortality in critically ill patients with severe COVID-19[J]. Nutrients, 2022, 14(10): 2105. doi:10.3390/nu14102105. |
| [24] | 朱莉. 预后营养指数在客家人炎症性肠病严重程度及复发的应用研究[J]. 中国中西医结合消化杂志, 2021, 29(12):873-878. |
| Zhu L. Application of prognostic nutritional index in the severity and recurrence of inflammatory bowel disease in Hakka[J]. Chinese Journal of Integrated Traditional and Western Medicine on Digestion, 2021, 29(12):873-878. doi:10.3969/j.issn.1671-038X.2021.12.008. | |
| [25] | Yang X, Ying S, Lv L, et al. Association between international normalized ratio-to-albumin ratio and mortality in critically ill patients with gastrointestinal bleeding: a retrospective MIMIC-IV database study[J]. BMC Gastroenterol, 2025, 25(1):574. doi:10.1186/s12876-025-04179-1. |
| [26] | Tian M, Yuan J, He P, et al. Monocyte-to-lymphocyte ratio and gastrointestinal disorder-related hospitalization in patients on maintenance hemodialysis[J]. Ther Apher Dial, 2024, 28(2):225-233. doi:10.1111/1744-9987.14073. |
| [27] | 苏小平, 徐静娟, 赵亚东, 等. 危重患者早期肠内营养喂养不耐受风险预测模型的构建[J]. 护理学报, 2022, 29(17):47-51. |
| Su X P, Xu J J, Zhao Y D, et al. Construction of a risk prediction model for early enteral nutrition feeding intolerance in critically ill patients[J]. Journal of Nursing, 2022, 29(17):47-51. | |
| [28] | Chen K, Yang D, Luo C. Early prediction of acute gastrointestinal injury in patients with acute pancreatitis by C-reactive protein/albumin ratio combined with IL-23[J]. Ann Clin Lab Sci, 2025, 55(2):224-230. |
| [29] | 彭小壮, 张晓敏. 重症监护室危重病人早期发生急性胃肠损伤的危险因素分析[J]. 临床外科杂志, 2025, 33(5):503-506. |
| Peng X Z, Zhang X M. Analysis of risk factors for early acute gastrointestinal injury in critically ill patients in the intensive care unit[J]. Journal of Clinical Surgery, 2025, 33(5):503-506. doi:10.3969/j.issn.1005-6483.20241463. |
| [1] | 张佳明, 班志超, 常黎明, 周医斋. 基于NFE2L1、TRIM26表达构建并验证预测免疫治疗转移性胃癌患者生存期的列线图模型[J]. 天津医药, 2026, 54(9): 934-940. |
| [2] | 焦宇兵, 雷晓娟, 郭武华. 自发性门体分流对乙型肝炎肝硬化失代偿期患者预后的影响及预测模型构建[J]. 天津医药, 2026, 54(6): 612-617. |
| [3] | 黄斐, 王利航, 孙官文, 包呼和, 杨鹏波, 张雅兴. 糖尿病足溃疡患者住院期间小截肢的预测模型构建及验证[J]. 天津医药, 2026, 54(5): 478-483. |
| [4] | 彭静, 余小倩. 结直肠癌术后患者肠内营养喂养不耐受的影响因素及预警模型的构建[J]. 天津医药, 2026, 54(5): 484-488. |
| [5] | 于波, 蒲肖琳, 刘乃婷, 李雅滨, 吴志茹. 消化道黏膜肿瘤患者EMR术后迟发性出血危险因素分析[J]. 天津医药, 2026, 54(5): 522-527. |
| [6] | 项亚娟, 陈长春, 张璐. 预后营养指数联合血清指标对急性脑梗死患者预后的预测价值[J]. 天津医药, 2026, 54(4): 423-428. |
| [7] | 李斌, 谭振刚, 张华清. 基于息肉特征和血清学指标构建结直肠息肉复发风险预测模型及效能分析[J]. 天津医药, 2026, 54(3): 249-253. |
| [8] | 朱海燕, 王烨, 尹艳. 老年NSCLC患者术后胃肠功能紊乱的危险因素研究[J]. 天津医药, 2026, 54(3): 289-294. |
| [9] | 刘晓华, 韩婷婷, 高玉杰. 增强CT淋巴结边缘特征联合IPI对难治性弥漫大B细胞巴瘤的预测价值[J]. 天津医药, 2026, 54(3): 303-308. |
| [10] | 文艺, 张君, 王英俊, 王铁锋, 董玉斌. 肺部超声评分及血清SP-A、IL-6水平与新生儿呼吸窘迫综合征病情及预后的相关性[J]. 天津医药, 2026, 54(2): 173-178. |
| [11] | 陈丽, 陈楠. COPD进展为Ⅱ型呼吸衰竭预警模型的建立与验证[J]. 天津医药, 2026, 54(2): 189-195. |
| [12] | 徐扬, 王永生, 王蕾, 储雪雁. 外周血NLR、PLR及CD4+/CD8+在结肠癌术后复发患者化疗前后的变化及与疗效的关系[J]. 天津医药, 2026, 54(11): 1172-1176. |
| [13] | 高兴, 李辰, 葛爽爽, 苗耐英. 血清MCP-1、TRAIL、CRP/ALb水平与新生儿坏死性小肠结肠炎患儿预后的关系[J]. 天津医药, 2026, 54(11): 1177-1182. |
| [14] | 钟杰林, 蔡迎, 金成浩, 苏啸天, 刘博, 李栩. 膝骨关节炎患者全膝关节置换术后恶心呕吐的影响因素预测模型建立与验证[J]. 天津医药, 2026, 54(11): 1209-1214. |
| [15] | 毛义翔, 王海东, 杭业, 宋锦. NSCLC患者放射治疗后发生症状性放射性肺炎的列线图预测模型构建及验证[J]. 天津医药, 2026, 54(10): 1081-1086. |
| 阅读次数 | ||||||
|
全文 |
|
|||||
|
摘要 |
|
|||||
