
Tianjin Medical Journal ›› 2024, Vol. 52 ›› Issue (9): 917-923.doi: 10.11958/20240171
• Experimental Research • Previous Articles Next Articles
GAO Pan( ), XIE Bingxin, ZHOU Zandong, LIU Tong△()
Received:2024-02-02
Revised:2024-04-16
Published:2024-09-15
Online:2024-09-06
Contact:
△E-mail:GAO Pan, XIE Bingxin, ZHOU Zandong, LIU Tong. Promoting effect of circulating FGF23 on atrial fibrosis in chronic kidney disease[J]. Tianjin Medical Journal, 2024, 52(9): 917-923.
CLC Number:
| 组别 | 体质量/g | Cr/ (μmol/L) | BUN/ (mmol/L) | 收缩压/ mmHg | |||
|---|---|---|---|---|---|---|---|
| SHAM组 | 485.60±38.28 | 23.57±8.18 | 168.09±8.66 | 114.17±4.78 | |||
| CKD组 | 502.80±28.88 | 58.05±13.57 | 245.09±19.83 | 126.17±6.11 | |||
| t | 0.802 | 4.866** | 7.955** | 3.460** | |||
| 组别 | 平均动脉压/ mmHg | 舒张压/ mmHg | 心脏质量/胫骨 长度/(mg/cm) | ||||
| SHAM组 | 100.73±2.31 | 93.94±3.28 | 31.20±4.04 | ||||
| CKD组 | 103.42±8.86 | 93.68±9.86 | 44.41±4.46 | ||||
| t | 0.657 | 0.057 | 4.907** | ||||
Tab.1 Comparison of biochemical indicators and baseline characteristics between the two groups of rats
| 组别 | 体质量/g | Cr/ (μmol/L) | BUN/ (mmol/L) | 收缩压/ mmHg | |||
|---|---|---|---|---|---|---|---|
| SHAM组 | 485.60±38.28 | 23.57±8.18 | 168.09±8.66 | 114.17±4.78 | |||
| CKD组 | 502.80±28.88 | 58.05±13.57 | 245.09±19.83 | 126.17±6.11 | |||
| t | 0.802 | 4.866** | 7.955** | 3.460** | |||
| 组别 | 平均动脉压/ mmHg | 舒张压/ mmHg | 心脏质量/胫骨 长度/(mg/cm) | ||||
| SHAM组 | 100.73±2.31 | 93.94±3.28 | 31.20±4.04 | ||||
| CKD组 | 103.42±8.86 | 93.68±9.86 | 44.41±4.46 | ||||
| t | 0.657 | 0.057 | 4.907** | ||||
| 组别 | QT间期/ms | 窦房结恢复时间/ms | 房颤持续时间/s |
|---|---|---|---|
| Sham组 | 41.60±8.29 | 170.00±8.72 | 1.16±2.59 |
| CKD组 | 86.80±10.73 | 206.40±25.63 | 10.02±6.56 |
| t | 7.451** | 3.007* | 2.807* |
Tab.2 Comparison of electrophysiologic parameters between two groups of rats
| 组别 | QT间期/ms | 窦房结恢复时间/ms | 房颤持续时间/s |
|---|---|---|---|
| Sham组 | 41.60±8.29 | 170.00±8.72 | 1.16±2.59 |
| CKD组 | 86.80±10.73 | 206.40±25.63 | 10.02±6.56 |
| t | 7.451** | 3.007* | 2.807* |
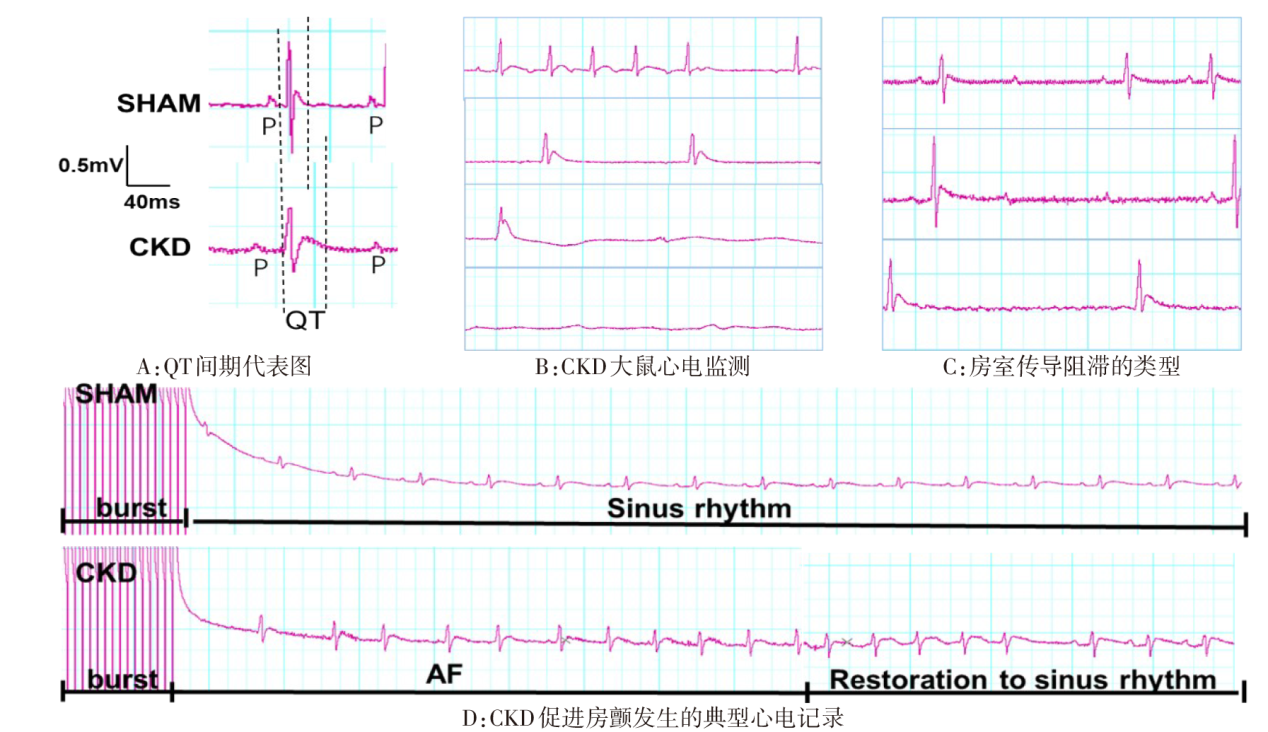
Fig.1 Electrophysiological study of electrocardiograms in two groups of rats
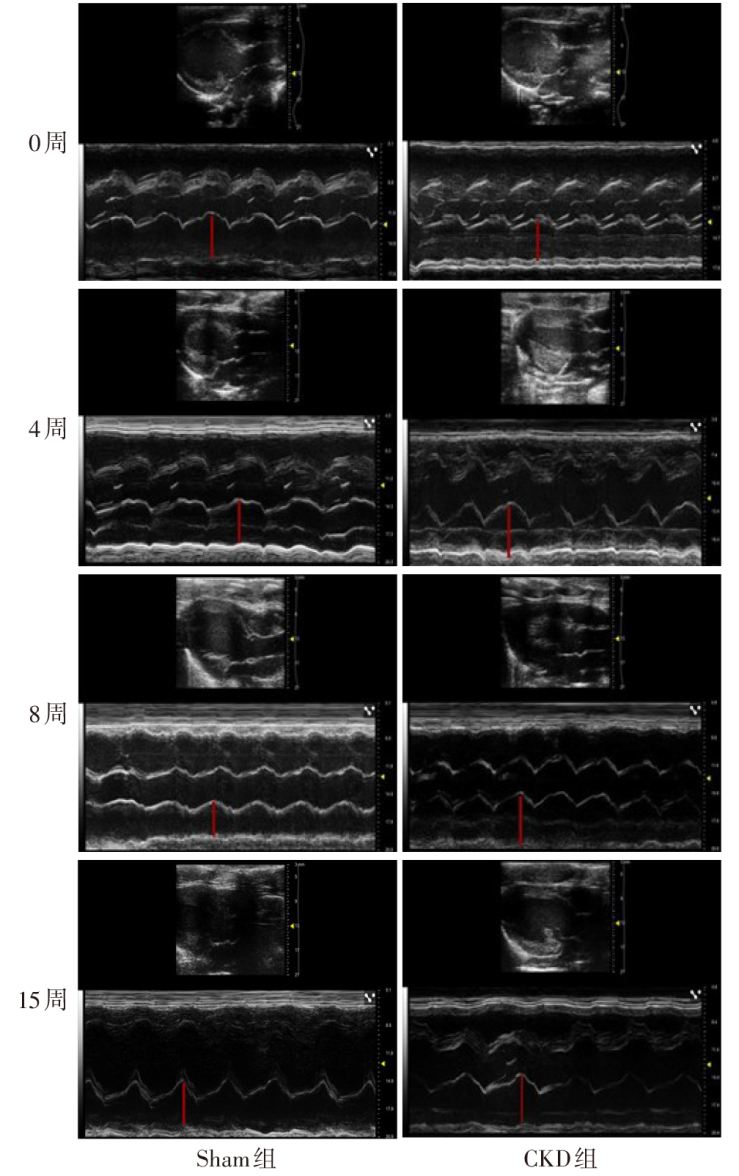
Fig.2 Changes in LAD at various time intervals in two groups of rats
| 组别 | 0周 | 4周 | 8周 | 15周 |
|---|---|---|---|---|
| SHAM组 | 3.96±0.12 | 3.95±0.36 | 3.96±0.34 | 4.00±0.40 |
| CKD组 | 3.98±0.35 | 4.63±0.16 | 4.67±0.38 | 4.81±0.10 |
| t | 0.131 | 3.909** | 3.128* | 4.381** |
Tab.3 Comparison of LAD in different time periods between two groups of rats
| 组别 | 0周 | 4周 | 8周 | 15周 |
|---|---|---|---|---|
| SHAM组 | 3.96±0.12 | 3.95±0.36 | 3.96±0.34 | 4.00±0.40 |
| CKD组 | 3.98±0.35 | 4.63±0.16 | 4.67±0.38 | 4.81±0.10 |
| t | 0.131 | 3.909** | 3.128* | 4.381** |
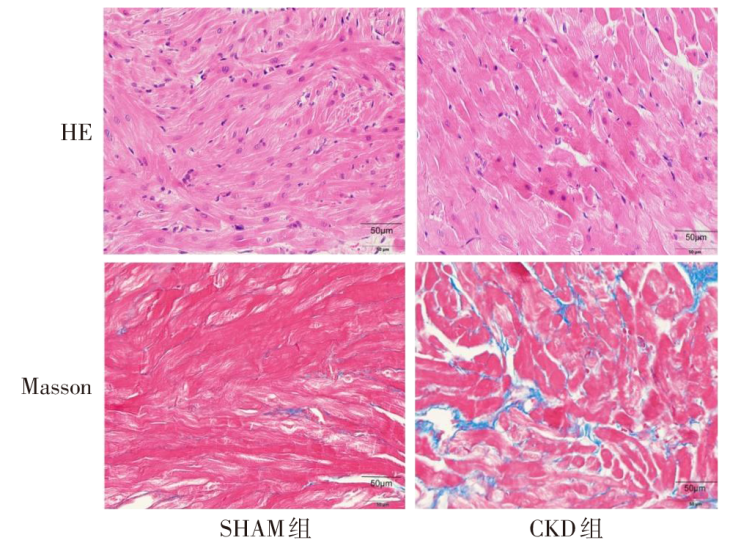
Fig.3 Pathological changes in left atrial tissue of rats in both groups (HE staining, Masson staining, ×400)
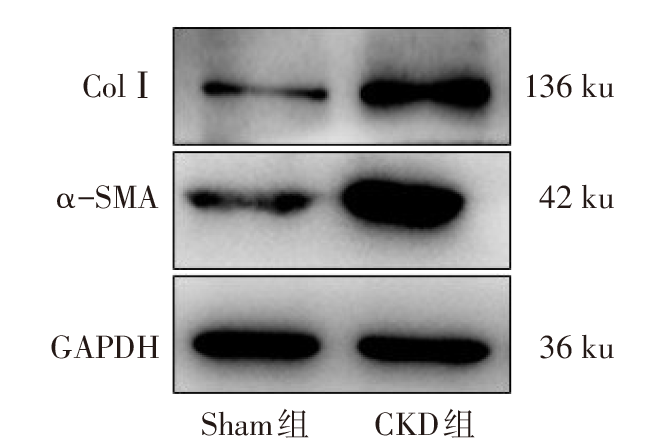
Fig.4 The expression levels of α-SMA and Col Ⅰ protein in left atrium of rats from two groups detected by Western blot assay
| 组别 | 组织胶原容积分数 | α-SMA | ColⅠ | 左心房传导速度/(mm/ms) | 绝对不均一性/(ms/mm) | 不均匀性指数 |
|---|---|---|---|---|---|---|
| Sham组 | 2.29±0.67 | 0.26±0.07 | 0.44±0.26 | 0.82±0.18 | 3.82±1.39 | 1.20±0.45 |
| CKD组 | 5.12±1.20 | 1.14±0.59 | 1.58±0.58 | 0.39±0.09 | 7.16±2.87 | 3.28±1.22 |
| t | 4.634** | 3.322* | 4.020** | 4.780** | 2.343* | 3.578** |
Tab.4 Comparison of structural remodeling as well as electrical remodeling parameters of atria between two groups of rats
| 组别 | 组织胶原容积分数 | α-SMA | ColⅠ | 左心房传导速度/(mm/ms) | 绝对不均一性/(ms/mm) | 不均匀性指数 |
|---|---|---|---|---|---|---|
| Sham组 | 2.29±0.67 | 0.26±0.07 | 0.44±0.26 | 0.82±0.18 | 3.82±1.39 | 1.20±0.45 |
| CKD组 | 5.12±1.20 | 1.14±0.59 | 1.58±0.58 | 0.39±0.09 | 7.16±2.87 | 3.28±1.22 |
| t | 4.634** | 3.322* | 4.020** | 4.780** | 2.343* | 3.578** |
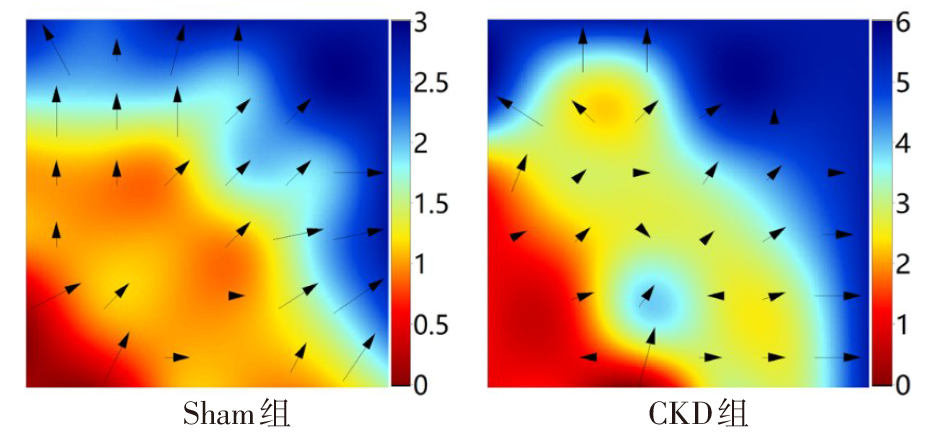
Fig.5 Typical diagram of left atrial epicardial electrical markers in two groups
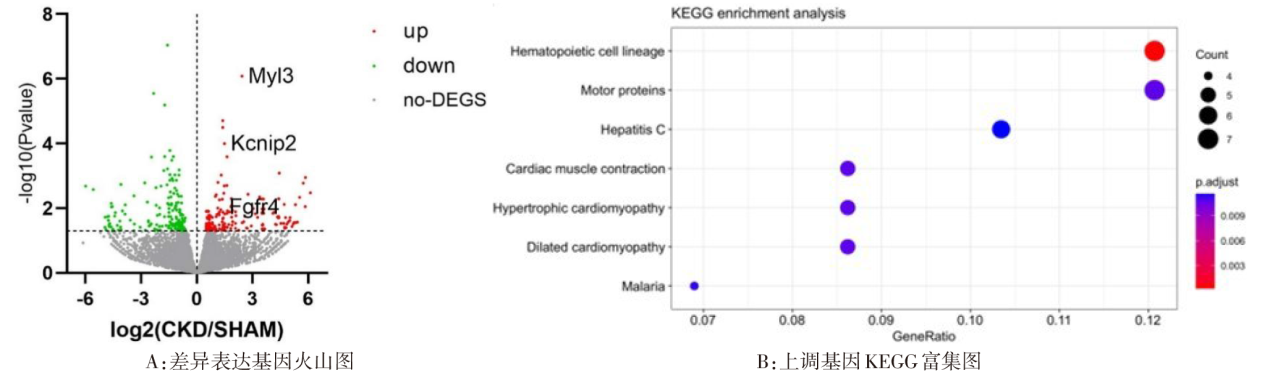
Fig.6 Results of bioinformatic analysis of differentially expressed genes
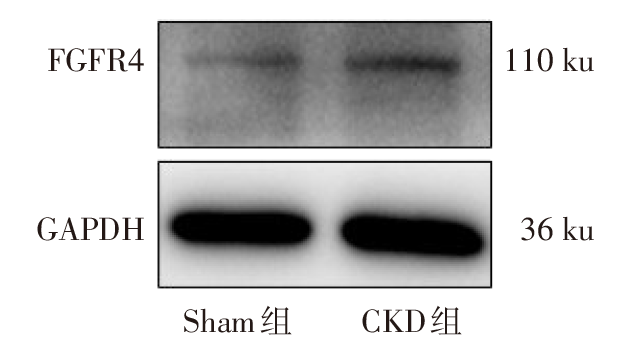
Fig.7 The expression of FGFR4 protein in left atrium of rats from two groups detected by Western blot assay
| 组别 | FGF23/(ng/L) | FGFR4 |
|---|---|---|
| Sham组 | 2 771.53±1 393.28 | 0.30±0.27 |
| CKD组 | 8 452.75±1 377.41 | 0.97±0.37 |
| t | 6.484** | 3.239* |
Tab.5 Comparison of circulating FGF23 levels and atrial FGFR4 protein expression between two groups of rats
| 组别 | FGF23/(ng/L) | FGFR4 |
|---|---|---|
| Sham组 | 2 771.53±1 393.28 | 0.30±0.27 |
| CKD组 | 8 452.75±1 377.41 | 0.97±0.37 |
| t | 6.484** | 3.239* |
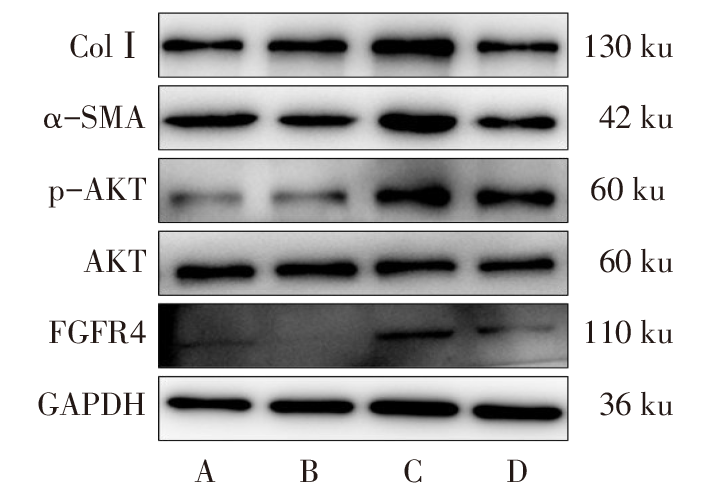
Fig.8 Western blot analysis of Col I, α-SMA, p-AKT, AKT and FGFR4 protein expression in each cell group
| 组别 | ColⅠ | α-SMA | FGFR4 | p-AKT/AKT |
|---|---|---|---|---|
| 对照组 | 0.46±0.10 | 0.36±0.18 | 0.41±0.08 | 0.79±0.27 |
| FGFR抑制剂组 | 0.44±0.13 | 0.41±0.16 | 0.27±0.20 | 0.60±0.28 |
| TGF-β组 | 0.97±0.11ab | 1.22±0.08ab | 1.19±0.39ab | 2.90±0.94ab |
| TGF-β+FGFR抑制剂组 | 0.58±0.25c | 0.72±0.08c | 0.43±0.16c | 0.34±0.20c |
| F | 22.585** | 37.142** | 12.359** | 20.705** |
Tab.6 Comparison of protein levels of α-SMA, Col I, FGFR4 and p-AKT between four groups of cells
| 组别 | ColⅠ | α-SMA | FGFR4 | p-AKT/AKT |
|---|---|---|---|---|
| 对照组 | 0.46±0.10 | 0.36±0.18 | 0.41±0.08 | 0.79±0.27 |
| FGFR抑制剂组 | 0.44±0.13 | 0.41±0.16 | 0.27±0.20 | 0.60±0.28 |
| TGF-β组 | 0.97±0.11ab | 1.22±0.08ab | 1.19±0.39ab | 2.90±0.94ab |
| TGF-β+FGFR抑制剂组 | 0.58±0.25c | 0.72±0.08c | 0.43±0.16c | 0.34±0.20c |
| F | 22.585** | 37.142** | 12.359** | 20.705** |
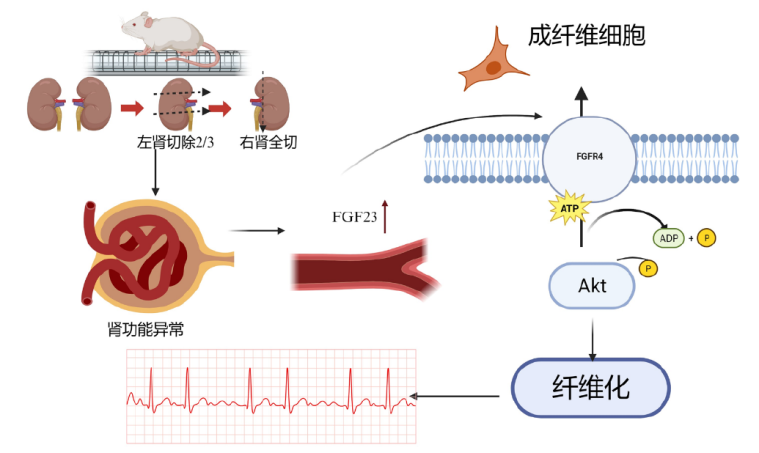
Fig.9 FGF23/FGFR4 downstream pathway illustration
| [1] | 高翔, 梅长林. 慢性肾脏病早期筛查、诊断及防治指南(2022年版)[J]. 中华肾脏病杂志, 2022, 38(5):453-464. |
| GAO X, MEI C L. Interpretation of guideline for early screening,diagnosis,prevention and treatment of chronic kidney disease(2022 edition)[J]. Chinese Journal of Practical Internal Medicine, 2022, 38(5):453-464. doi:10.19538/j.nk2022090108. | |
| [2] | GREGG L P, HEDAYATI S S. Management of traditional cardiovascular risk factors in CKD:what are the data?[J]. Am J Kidney Dis, 2018, 72(5):728-744. doi:10.1053/j.ajkd.2017.12.007. |
| [3] | BANSAL N, FAN D, HSU C Y, et al. Incident atrial fibrillation and risk of end-stage renal disease in adults with chronic kidney disease[J]. Circulation, 2013, 127(5):569-574. doi:10.1161/CIRCULATIONAHA.112.123992. |
| [4] | LIPPI G, SANCHIS-GOMAR F, CERVELLIN G. Global epidemiology of atrial fibrillation:an increasing epidemic and public health challenge[J]. Int J Stroke, 2021, 16(2):217-221. doi:10.1177/1747493019897870. |
| [5] | SOLIMAN E Z, PRINEAS R J, GO A S, et al. Chronic kidney disease and prevalent atrial fibrillation:the Chronic Renal Insufficiency Cohort (CRIC)[J]. Am Heart J, 2010, 159(6):1102-1107. doi:10.1016/j.ahj.2010.03.027. |
| [6] | GUO Y, GAO J, YE P, et al. Comparison of atrial fibrillation in CKD and non-CKD populations:a cross-sectional analysis from the Kailuan study[J]. Int J Cardiol, 2019, 277:125-129. doi:10.1016/j.ijcard.2018.11.098. |
| [7] | DING W Y, GUPTA D, WONG C F, et al. Pathophysiology of atrial fibrillation and chronic kidney disease[J]. Cardiovasc Res, 2021, 117(4):1046-1059. doi:10.1093/cvr/cvaa258. |
| [8] | JANKOWSKI J, FLOEGE J, FLISER D, et al. Cardiovascular disease in chronic kidney disease:pathophysiological insights and therapeutic options[J]. Circulation, 2021, 143(11):1157-1172. doi:10.1161/CIRCULATIONAHA.120.050686. |
| [9] | KOVESDY C P. Epidemiology of chronic kidney disease: an update 2022[J]. Kidney Int Suppl (2011), 2022, 12(1):7-11. doi:10.1016/j.kisu.2021.11.003. |
| [10] | MATHEW J S, SACHS M C, KATZ R, et al. Fibroblast growth factor-23 and incident atrial fibrillation:the Multi-Ethnic Study of Atherosclerosis (MESA) and the Cardiovascular Health Study (CHS)[J]. Circulation, 2014, 130(4):298-307. doi:10.1161/CIRCULATIONAHA.113.005499. |
| [11] | FAUL C, AMARAL A P, OSKOUEI B, et al. FGF23 induces left ventricular hypertrophy[J]. J Clin Invest, 2011, 121(11):4393-4408. doi:10.1172/JCI46122. |
| [12] | DONG Q, LI S, WANG W, et al. FGF23 regulates atrial fibrosis in atrial fibrillation by mediating the STAT3 and SMAD3 pathways[J]. J Cell Physiol, 2019, 234(11):19502-19510. doi:10.1002/jcp.28548. |
| [13] | YAO C, VELEVA T, SCOTT L J R, et al. Enhanced cardiomyocyte NLRP3 inflammasome signaling promotes atrial fibrillation[J]. Circulation, 2018, 138(20):2227-2242. doi:10.1161/CIRCULATIONAHA.118.035202. |
| [14] | HEALEY J S, BARANCHUK A, CRYSTAL E, et al. Prevention of atrial fibrillation with angiotensin-converting enzyme inhibitors and angiotensin receptor blockers:a Meta-analysis[J]. J Am Coll Cardiol, 2005, 45(11):1832-1839. doi:10.1016/j.jacc.2004.11.070. |
| [15] | LANDRAY M J, WHEELER D C, LIP G Y, et al. Inflammation,endothelial dysfunction,and platelet activation in patients with chronic kidney disease:the chronic renal impairment in Birmingham (CRIB) study[J]. Am J Kidney Dis, 2004, 43(2):244-253. doi:10.1053/j.ajkd.2003.10.037. |
| [16] | SONG J, NAVARRO-GARCIA J A, WU J, et al. Chronic kidney disease promotes atrial fibrillation via inflammasome pathway activation[J]. J Clin Invest, 2023, 133(19):e167517. doi:10.1172/JCI167517. |
| [17] | QIU H, JI C, WU H, et al. Chronic kidney disease-induced atrial structural remodeling and atrial fibrillation: more studies on the pathological mechanism are encouraged[J]. Naunyn Schmiedebergs Arch Pharmacol, 2018, 391(7):671-673. doi:10.1007/s00210-018-1494-4. |
| [18] | AOKI K, TESHIMA Y, KONDO H, et al. Role of indoxyl sulfate as a predisposing factor for atrial fibrillation in renal dysfunction[J]. J Am Heart Assoc, 2015, 4(10):e002023. doi:10.1161/JAHA.115.002023. |
| [19] | HEIJMAN J, VOIGT N, GHEZELBASH S, et al. Calcium handling abnormalities as a target for atrial fibrillation therapeutics:how close to clinical implementation?[J]. J Cardiovasc Pharmacol, 2015, 66(6):515-522. doi:10.1097/FJC.0000000000000253. |
| [20] | CHEN W T, CHEN Y C, HSIEH M H, et al. The uremic toxin indoxyl sulfate increases pulmonary vein and atrial arrhythmogenesis[J]. J Cardiovasc Electrophysiol, 2015, 26(2):203-210. doi:10.1111/jce.12554. |
| [21] | KUGA K, KUSAKARI Y, UESUGI K, et al. Fibrosis growth factor 23 is a promoting factor for cardiac fibrosis in the presence of transforming growth factor-β1[J]. PLoS One, 2020, 15(4):e0231905. doi:10.1371/journal.pone.0231905. |
| [22] | LEIFHEIT-NESTLER M, KIRCHHOFF F, NESPOR J, et al. Fibroblast growth factor 23 is induced by an activated renin-angiotensin-aldosterone system in cardiac myocytes and promotes the pro-fibrotic crosstalk between cardiac myocytes and fibroblasts[J]. Nephrol Dial Transplant, 2018, 33(10):1722-1734. doi:10.1093/ndt/gfy006. |
| [23] | GRABNER A, AMARAL A P, SCHRAMM K, et al. Activation of cardiac fibroblast growth factor receptor 4 causes left ventricular hypertrophy[J]. Cell Metab, 2015, 22(6):1020-1032. doi:10.1016/j.cmet.2015.09.002. |
| [24] | HAN X, CAI C, XIAO Z, et al. FGF23 induced left ventricular hypertrophy mediated by FGFR4 signaling in the myocardium is attenuated by soluble Klotho in mice[J]. J Mol Cell Cardiol, 2020, 138:66-74. doi:10.1016/j.yjmcc.2019.11.149. |
| [25] | SINGH S, GRABNER A, YANUCIL C, et al. Fibroblast growth factor 23 directly targets hepatocytes to promote inflammation in chronic kidney disease[J]. Kidney Int, 2016, 90(5):985-996. doi:10.1016/j.kint.2016.05.019. |
| Viewed | ||||||
|
Full text |
|
|||||
|
Abstract |
|
|||||
